5 Clinical Concepts Every Nurse Should Understand
Nursing school teaches you hundreds of diseases, medications, lab values, procedures, and nursing interventions. But becoming strong clinically requires more than memorizing individual facts.
The real skill is learning how to connect the information together.
Why is the patient’s blood pressure dropping? What does an increasing respiratory rate tell you? Why are the kidneys suddenly producing less urine? Which finding matters most right now?
Understanding a few foundational clinical concepts can make it much easier to recognize when a patient is deteriorating and understand why certain nursing interventions are being performed.
Here are 5 clinical concepts every nurse should understand.
Related Content:
- How to Register for the NCLEX Step-by-Step in 2026 https://choosingnursing.net/how-to-register-for-the-nclex-step-by-step-in-2026/
- NCLEX Prioritization and Delegation Made Easy: How to Answer These Questions with Confidence https://choosingnursing.net/nclex-prioritization-and-delegation/
- 2026 NCLEX Updates Every Nursing Candidate Needs to Know https://choosingnursing.net/2026-nclex-updates/
- How To Pass The Nclex After Failing (Without Feeling Overwhelmed) https://choosingnursing.net/how-to-pass-the-nclex-after-failing/
- Good Pop-Up vs Bad Pop-Up After the NCLEX https://choosingnursing.net/good-pop-up-vs-bad-pop-up-nclex/
1. Perfusion: Is Blood Actually Reaching the Tissues?
Perfusion is one of the most important concepts in nursing.
Simply put, perfusion is the delivery of oxygenated blood to the body’s tissues and organs.
A patient can technically have a heartbeat and still have inadequate tissue perfusion.
When perfusion decreases, organs may not receive enough oxygen and nutrients to function normally. If the problem continues, tissue injury and organ dysfunction can occur.
Signs of poor perfusion can include:
- Hypotension
- Tachycardia
- Weak peripheral pulses
- Cool or clammy skin
- Delayed capillary refill
- Altered mental status
- Decreased urine output
- Elevated lactate
- Dizziness or weakness
One of the most useful ways to think about perfusion is through cardiac output.
Cardiac Output = Heart Rate × Stroke Volume
Stroke volume is the amount of blood pumped from the ventricle with each contraction.
This means anything that significantly affects heart rate or stroke volume can affect cardiac output—and therefore perfusion.
For example, consider a patient who is actively bleeding.
Blood volume decreases → venous return decreases → stroke volume decreases → cardiac output may decrease → tissue perfusion decreases.
The nurse might initially notice:
HR 118 → BP 92/56 → cool skin → decreasing urine output
Instead of seeing four unrelated findings, you should begin recognizing a pattern:
This patient may not be perfusing adequately.
Clinical takeaway
When assessing a potentially unstable patient, ask yourself:
“Are the patient’s organs receiving enough blood and oxygen?”
That single question can help you connect vital signs, mental status, urine output, skin findings, and laboratory results.
Recommended Reading
How to Understand Med Surg: A Nursing Student’s Guide to Actually Learning Medical-Surgical Nursing
2. Oxygenation vs. Ventilation
These terms are often used together, but they are not the same thing.
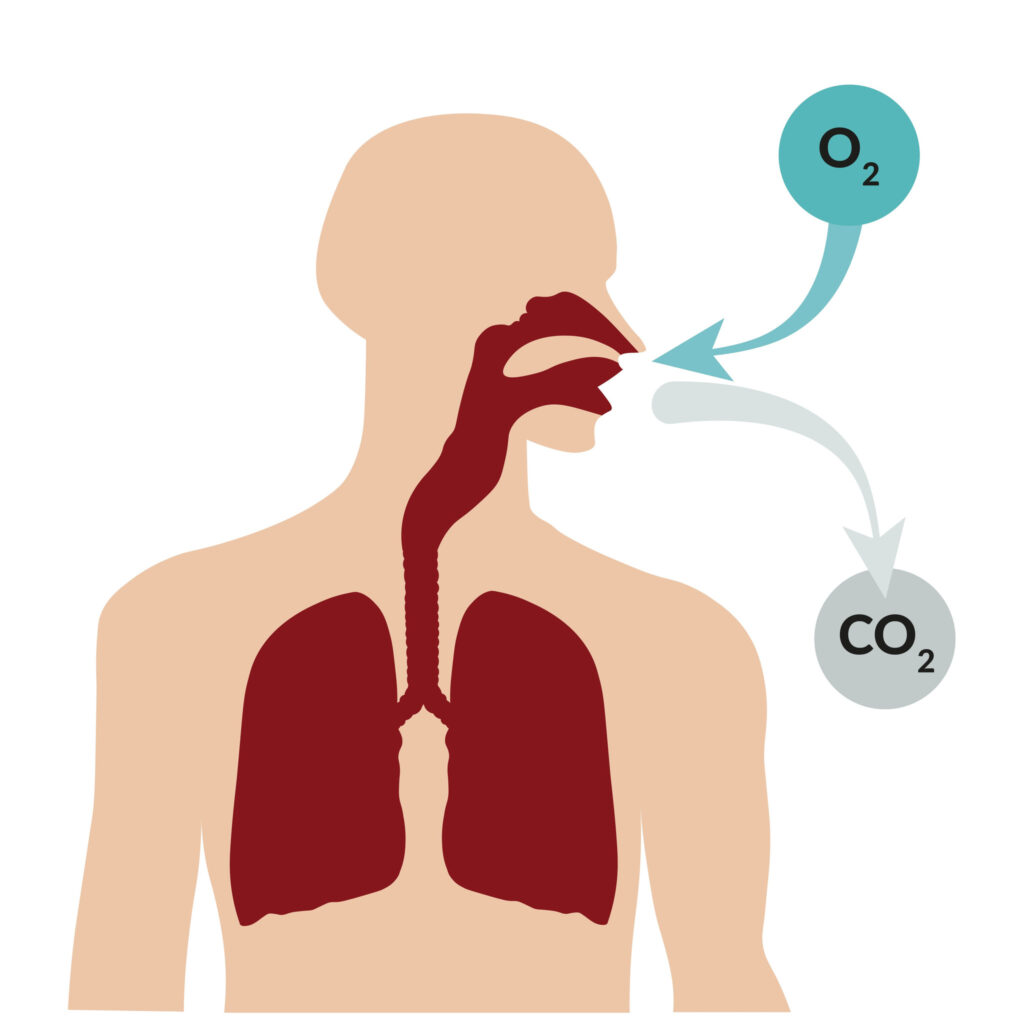
Oxygenation refers to getting oxygen into the blood.
Ventilation refers to moving air in and out of the lungs and removing carbon dioxide.
A patient can have problems with one, the other, or both.
Oxygenation problems
Conditions that interfere with oxygen moving from the lungs into the bloodstream may include:
- Pneumonia
- Pulmonary edema
- Acute respiratory distress syndrome (ARDS)
- Pulmonary embolism
- Atelectasis
- Severe lung disease
Signs may include decreasing oxygen saturation, cyanosis, restlessness, tachypnea, or increased work of breathing.
Ventilation problems
Ventilation becomes impaired when the patient cannot adequately move air.
This may occur with:
- Opioid-induced respiratory depression
- Severe COPD
- Neuromuscular weakness
- Airway obstruction
- Central nervous system depression
Carbon dioxide may begin accumulating in the blood.
This is why SpO₂ does not tell you everything about respiratory status.
A patient may have an acceptable oxygen saturation while still ventilating poorly, particularly if supplemental oxygen is being administered.
Don’t ignore respiratory rate
Respiratory rate can be an important early sign of deterioration.
A patient whose respiratory rate changes from:
18 → 24 → 30 breaths/min
may be compensating for a developing problem even before other vital signs become dramatically abnormal.
Always look at the entire respiratory picture:
Respiratory rate + oxygen saturation + work of breathing + mental status + breath sounds + relevant blood gases
Clinical takeaway
Don’t only ask:
“Is the oxygen saturation normal?”
Also ask:
“Is this patient moving air effectively?”
3. Fluid Volume and Electrolyte Balance
Fluids and electrolytes affect nearly every organ system.
A relatively small imbalance can sometimes create major clinical consequences.
Nurses should understand the difference between fluid volume deficit and fluid volume excess.
Fluid volume deficit
Possible causes include:
- Vomiting
- Diarrhea
- Hemorrhage
- Excessive sweating
- Poor oral intake
- Diuretic use
- Burns
Possible findings include:
- Tachycardia
- Hypotension
- Dry mucous membranes
- Decreased urine output
- Weakness
- Dizziness
- Poor skin turgor
Fluid volume excess
Possible causes include:
- Heart failure
- Kidney dysfunction
- Excessive IV fluid administration
- Certain liver conditions
Possible findings include:
- Peripheral edema
- Crackles
- Shortness of breath
- Rapid weight gain
- Jugular venous distention
- Hypertension in some patients
Daily weight can be extremely useful when monitoring fluid status.
Approximately 1 kilogram (2.2 pounds) of acute weight change can represent about 1 liter of fluid, although clinical interpretation should always consider the patient’s overall condition.
Electrolytes matter too
Electrolytes such as potassium, sodium, calcium, and magnesium play important roles in cardiac, neurological, and muscular function.
For example, abnormal potassium levels can affect cardiac conduction and increase the risk of dysrhythmias.
Instead of simply memorizing normal ranges, ask:
What does this electrolyte do in the body?
Then ask:
What happens when there is too much or too little?
That approach makes electrolyte disorders much easier to understand.
4. Acid-Base Balance
ABGs can look intimidating at first, but the basic concept is much simpler when you understand what the body is trying to accomplish.
The body works constantly to maintain a relatively narrow blood pH.
Two major systems help regulate acid-base balance:
The lungs regulate carbon dioxide.
The kidneys regulate bicarbonate and hydrogen ions.
This gives you a useful shortcut:
CO₂ = respiratory component
HCO₃⁻ = metabolic component
The four primary acid-base disorders are:
- Respiratory acidosis
- Respiratory alkalosis
- Metabolic acidosis
- Metabolic alkalosis
Example: respiratory acidosis
Imagine a patient receiving opioids who becomes extremely drowsy and begins breathing only 6 times per minute.
The patient is not adequately ventilating.
CO₂ begins accumulating.
CO₂ increases → acidity increases → pH decreases.
That pattern can produce respiratory acidosis.
Example: metabolic acidosis
Consider a patient with diabetic ketoacidosis (DKA).
The body cannot effectively use glucose because of insufficient insulin. It begins breaking down fat, producing acidic ketones.
As acids accumulate, the pH decreases.
The respiratory system may attempt to compensate by increasing ventilation, which can produce the deep, rapid breathing associated with DKA.
The key is understanding the physiology rather than simply memorizing ABG patterns.
Clinical takeaway
When looking at an abnormal ABG, ask:
Is the primary problem respiratory or metabolic?
Then determine whether the body appears to be compensating.
5. Compensation and Patient Deterioration
One of the most important concepts in bedside nursing is understanding that patients can look relatively stable while their bodies are working extremely hard to keep them stable.
This is compensation.
When something begins going wrong, the body activates mechanisms designed to maintain oxygen delivery, blood pressure, pH, and organ function.
For example, when circulating blood volume decreases, the body may increase the heart rate and constrict peripheral blood vessels.
The patient’s blood pressure may initially remain within an acceptable range.
That does not necessarily mean the patient is fine.
Consider this trend:
10:00 AM
HR: 88
BP: 122/74
RR: 18
12:00 PM
HR: 104
BP: 110/68
RR: 22
2:00 PM
HR: 122
BP: 94/58
RR: 28
Looking at any single vital sign without context could cause you to miss the larger picture.
Looking at the trend tells a different story.
The patient is deteriorating.
This is why experienced nurses often pay close attention to changes rather than simply asking whether a value technically falls inside a normal range.
Look for clusters
One abnormal finding may not tell you much.
Several related findings can tell you a lot.
For example:
Tachycardia + hypotension + confusion + decreased urine output
should immediately make you think about decreased perfusion and possible shock.
Similarly:
Increasing respiratory rate + decreasing oxygen saturation + restlessness + increased work of breathing
may indicate worsening respiratory compromise.
Clinical takeaway
Don’t only ask:
“Is this value abnormal?”
Ask:
“What direction is this patient moving?”
How to Think Like a Nurse: Connect the Concepts
The most important part of clinical reasoning is realizing that these concepts rarely occur independently.
Imagine a patient with severe sepsis.
Infection triggers a systemic response.
Blood vessels dilate and vascular permeability can increase.
Effective circulating volume and blood pressure may decrease.
Perfusion falls.
The kidneys receive less blood.
Urine output decreases.
Cells may shift toward anaerobic metabolism.
Lactate can rise.
Acid-base disturbances may develop.
The respiratory rate increases as the body attempts to compensate.
Now several concepts are happening simultaneously:
Perfusion → Fluid balance → Oxygen delivery → Acid-base balance → Compensation
This is why understanding the underlying concepts can be more powerful than memorizing isolated facts.



A Simple Clinical Reasoning Framework
When you’re reviewing a patient, try asking yourself these five questions:
- Perfusion: Is blood adequately reaching the organs?
- Respiration: Is the patient oxygenating and ventilating effectively?
- Fluid/Electrolytes: Is the patient’s fluid and electrolyte balance appropriate?
- Acid-Base: Is the body maintaining normal pH?
- Compensation: Is the body compensating for a developing problem?
Then ask one final question:
“Is this patient getting better, getting worse, or staying the same?”
That question encourages you to think in trends instead of snapshots.
Final Thoughts
Strong clinical judgment doesn’t come from memorizing every disease in a textbook.
It develops when you understand the physiological concepts underneath those diseases and learn how to recognize patterns.
Perfusion, oxygenation and ventilation, fluid and electrolyte balance, acid-base balance, and compensation appear repeatedly across medical-surgical nursing, critical care, emergency nursing, pharmacology, and NCLEX-style questions.
When you understand these concepts, conditions that once seemed completely unrelated begin connecting.
Heart failure makes more sense.
Shock makes more sense.
DKA makes more sense.
Respiratory failure makes more sense.
Kidney injury makes more sense.
And instead of simply memorizing what happens to a patient, you begin understanding why it happens.
That is where clinical reasoning starts.
Continue Building Your Nursing Knowledge
If you’re working on strengthening your clinical knowledge, don’t stop with individual disease definitions. Focus on understanding how assessment findings, pathophysiology, medications, laboratory values, and nursing interventions connect.
Explore our Nursing Student Resources for additional study guides, nursing articles, videos, clinical concepts, and educational resources designed to help you strengthen your nursing knowledge.
Educational Disclaimer: This article is intended for nursing education and general informational purposes only. It does not replace facility protocols, clinical judgment, individualized medical advice, or guidance from a qualified healthcare professional.
